
1
We test segment by segment.
Hands-on work for the spinal joint that has stopped moving the way it should. One technique among several, used when the evaluation says it is indicated, inside a plan with an endpoint.
What It Is
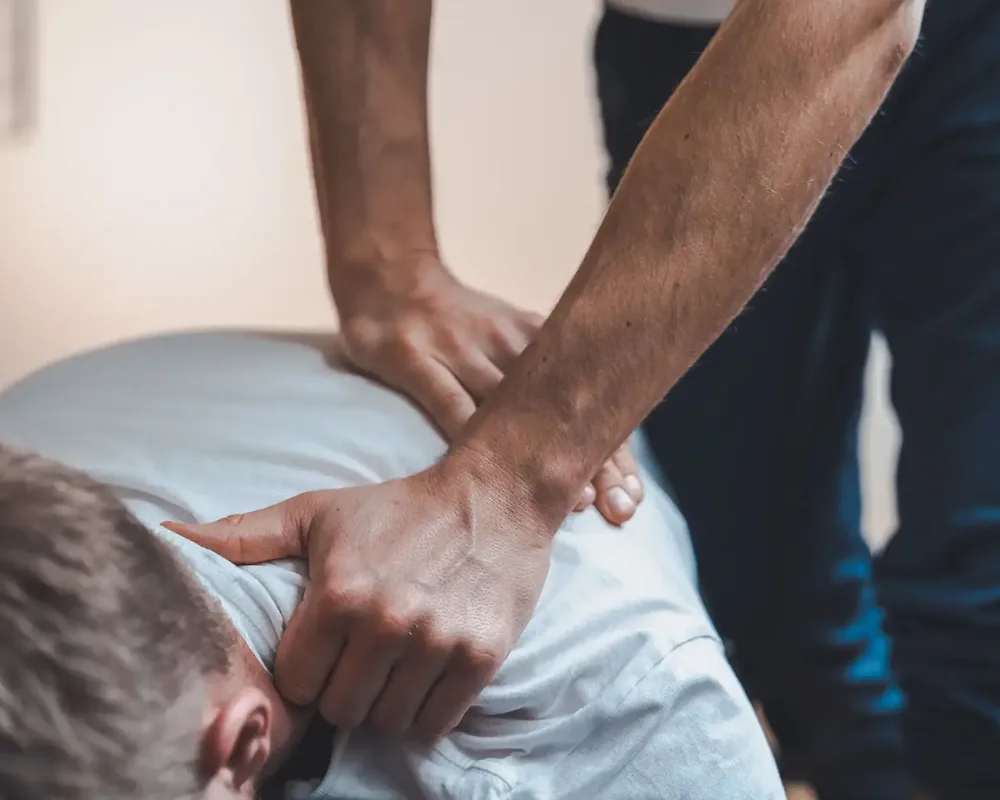
Your spine is a stack of joints, and like any joint they can stop moving through their full range. A segment that has stiffened changes how the segments above and below have to work, and the muscles around it tighten to protect it. Spinal manipulation is skilled hands-on work applied to that segment: either a graded mobilisation, which is a slow, controlled pressure you can stop at any point, or a manipulation, which is a small quick thrust at the end of the available range. The two live on the same spectrum and get chosen by what the joint needs, not by preference.
Sometimes there is an audible pop. That sound is a pressure change in the joint fluid, closer to opening a bottle than to a bone going back into place. Nothing was out of alignment waiting to be reset. Plenty of successful treatments are silent, and a loud one is not a better one. What we test afterward is whether the segment moves better and whether you can do something you could not do five minutes earlier.
It is one technique among several, and it is never the whole plan. Manipulation buys a window: less pain, more range, a spine that will tolerate loading. What you do with that window, the mobility and the strength work in the same visit, is what decides whether the joint stays that way. Dr. Cheryl Thomas leads the spine caseload here and is trained in the McKenzie Method, a system built around finding which direction of movement actually changes your symptoms, which is exactly the kind of information that tells us whether manipulation belongs in your plan at all.
Everything runs through four named phases, Pain, Prime, Perform, and Prevent, in that order, one-on-one with a Doctor of Physical Therapy, with an endpoint named out loud at your evaluation.
 One technique, chosen on purpose
What It Helps
It is most useful where the evaluation traces the pain to a stiff, irritable spinal segment rather than to a nerve, a disc, or a muscle that needs strengthening. A sample of what it commonly supports:
A segment that has stopped moving does not stay a local problem. The joints above and below take on the range it gave up, the muscles around it stay switched on to protect it, and a year later the complaint has moved to a shoulder blade or a hip that was only ever covering for the spine.
What A Session Looks Like
1
We test segment by segment.
2
Seconds of technique, no surprises.
3
Retest, then load the change.
It happens inside a regular visit, not as a separate appointment. Your doctor screens first, then tests segment by segment with their hands to find which levels have actually lost range and which ones are only tender. Only then does the technique get chosen, and you are told what is about to happen and what it will feel like before anything moves.
The technique itself takes seconds. You are positioned, asked to breathe out, and given either a sustained pressure or a short, quick, low-amplitude thrust. It should not hurt. Then you are retested on the spot, because a technique that did not change anything measurable is one we stop using rather than repeat. The rest of the visit goes to the mobility and loading work that keeps the change, which is the part that actually decides how long it lasts.
Who It’s For
A stiff, irritable spinal segment found on examination, not just a sore spot.
Back, neck, or mid-back pain that limits what else can be done in the visit.
Comfortable with it being one technique among several inside a plan.
Willing to spend the rest of the visit on what makes the change hold.
Spinal manipulation fits people whose evaluation finds a genuinely stiff, irritable segment: a back that will not turn one way, a neck that has quietly given up its blind-spot check, a mid-back that catches on a deep breath. It is often most useful early, when pain is limiting what else can be done in the visit. You do not need a referral to be evaluated for it.
If you have been getting adjusted somewhere for two years and are wondering why it never quite finishes, that is not disloyalty. That is the correct question, and it has an answer: relief that has to be renewed weekly is relief the strength work was never added to.
It is not for everyone, and it is not always the right tool even for people it is safe for. We screen for osteoporosis, recent fracture or significant trauma, spinal instability, inflammatory joint disease, certain vascular findings, and the signs that pain is coming from something other than a joint: progressive weakness, changes in bowel or bladder control, unexplained weight loss, or night pain that wakes you and will not settle. Any of those and we stop, say so plainly, and help you get to the physician who should see it.
Great place and service. My therapist Cheryl is awesome. Explains everything in detail to my understanding.
Pairs Well With
Each of these is a tool inside the plan. None of them is the plan.
Questions, Answered
The hands-on technique overlaps a great deal. What differs is the context it sits in. Here it is one technique inside a physical therapy plan with four phases and a named endpoint, chosen because your evaluation said the joint was the problem, and paired the same visit with the mobility and strength work meant to keep it from stiffening again. It is not a standing weekly appointment, and it is not the plan by itself.
It is a pressure change in the fluid inside the joint, closer to opening a bottle than to anything moving back into place. Nothing is being reset, and nothing was out of alignment waiting to be put back. The sound is also not the goal: plenty of successful treatments are quiet, and a loud one does not mean a better result. What we look for afterward is a change in how the segment moves and what you can do with it.
For most people it is well tolerated, and screening is what makes it so. Before any manipulation your Doctor of Physical Therapy screens your history and your symptoms for the reasons not to do it: osteoporosis, recent fracture or trauma, instability, inflammatory joint disease, certain vascular findings, and any sign that the pain is not coming from a joint at all. If the screening says no, we say no, and we use one of the other techniques we have.
No, and that is deliberate. If a joint keeps stiffening back into the same restriction, the answer is not more frequent manipulation; it is finding what keeps loading it that way, which is what the strength and movement work in the later phases is for. Your plan has an endpoint named at the evaluation. Needing an indefinite series of adjustments to stay comfortable is a sign the underlying cause has not been addressed.
Book Your Visit
Five short questions. A real person from our front desk calls you back with times that fit your week. No phone tree, no ‘someone will reach out.’ Rather pick a slot yourself? Book online any time.
5.0 · 94 Google reviews
A real person calls you back during office hours
Step 1 of 5
That’s the hard part done. We’ll call during business hours to lock in your time.
Visit Us
Suite 203 on Cypress Creek Road in Cedar Park, open Monday to Friday from seven. Come see the place before you commit, if you like.